The 50,000-Image Diagnostic Bottleneck
Wireless capsule endoscopy (WCE) is one of the greatest innovations in gastrointestinal medicine, offering a non-invasive window into the deep twists of the small intestine. However, for the gastroenterologists tasked with reading these exams, the technology presents a major operational challenge: data overload.
Plaintext
[ The Diagnostic Bottleneck in Traditional Capsule Reading ]
------------------------------------------------------------
1 Capsule Ingestion  -->  8 to 14 Hours of Video Recording
                     -->  50,000 to 100,000 Individual Frames
                     -->  60 to 90 Minutes of Continuous Human Review
                     -->  Eye Strain, Mental Fatigue & Risk of Missed Lesions
------------------------------------------------------------
A capsule moves passively through the gastrointestinal tract, taking multiple pictures every second. While this guarantees comprehensive coverage, the vast majority of these frames show normal mucosal lining, motionless segments, or views obscured by digestive fluid and intestinal debris.
A physician must review this lengthy video stream frame by frame. After 30 to 45 minutes of continuous screening, reader fatigue naturally sets in. Subtle, life-threatening pathologies—such as a single bleeding angioectasia, an early Crohn’s aphthous ulcer, or a flat malignant polyp—may appear in only two or three frames out of 60,000.
To overcome this diagnostic bottleneck, medical imaging developers turned to Artificial Intelligence (AI), Computer Vision, and Cloud Tele-Endoscopy.

2. How Artificial Intelligence (AI) Analyzes Capsule Images
Modern capsule reading workstations are no longer simple video players. They are powered by advanced Convolutional Neural Networks (CNNs) and deep learning models trained on millions of clinically verified gastrointestinal images.
Plaintext
                      HOW AI REVIEWS CAPSULE FOOTAGE
                                    |
     +------------------------------+------------------------------+
     |                                                             |
     v                                                             v
[ REDUNDANT FRAME PURGING ]                       [ PATHOLOGY DETECTION & FLAGGING ]
- Deletes uninformative motionless frames         - Color analysis detects active bleeding
- Filters bile fluid, bubbles & food debris       - Texture analysis spots ulcers & erosions
- Retains only diagnostically relevant mucosa     - Morphology models detect polyps & tumors
A. Redundant Frame Filtering (Smart De-Duplication)
The digestive tract is not a smooth, uniformly moving conveyor belt. The capsule often lingers in the same fold of the stomach or small bowel for minutes at a time, capturing thousands of identical pictures.
-
AI algorithms evaluate spatial motion vectors between sequential frames. If five hundred consecutive frames show the exact same piece of tissue without change, the AI compresses or skips them.
-
Frames obscured by opaque bile, dense stool debris, or air bubbles are automatically tagged as low-diagnostic quality and separated from clear mucosal views.
-
This filtering removes up to 70% to 85% of redundant video frames, preserving the clinician’s attention for unique, diagnostically relevant anatomy.
B. Automated Bleeding Detection (Smart Red Sense)
Early software attempted to find bleeding using basic color thresholding, which resulted in countless false alarms caused by red foods (such as tomato skin or red fruit juices).
-
Modern deep learning models analyze contextual vascular morphology alongside color. The algorithm distinguishes between free blood pooling, active vascular jet bleeding, and harmless red food matter.
-
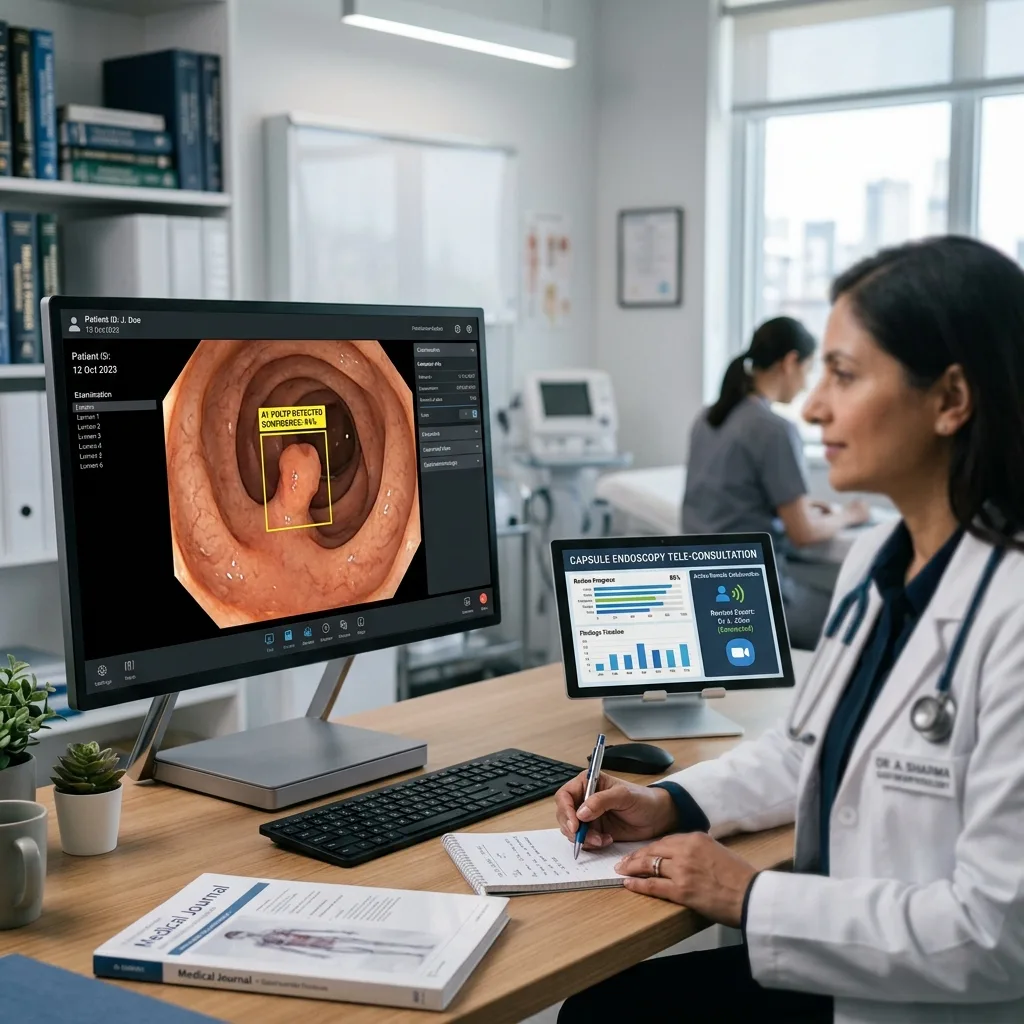
When bleeding or vascular malformations (like arteriovenous malformations or angiodysplasias) are identified, the software automatically places markers on the navigation timeline and compiles the suspicious frames into an “Emergency Review Gallery.”
C. Ulcer and Mucosal Erosion Identification
In inflammatory conditions like Crohn’s disease or NSAID-induced enteropathy, mucosal breaks can be minuscule.
-
AI models are trained to detect disruptions in mucosal texture, mucosal erythema (redness), whitish fibrinous exudate, and loss of normal villous architecture.
-
The system calculates a mucosal inflammation index, helping physicians score the severity of Crohn’s disease and monitor mucosal healing over time.
D. Polyp, Nodule, and Tumor Detection
Protruding lesions, such as adenomatous polyps, hamartomas, neuroendocrine tumors, and Gastrointestinal Stromal Tumors (GIST), present with subtle mucosal elevation.
-
AI computer vision evaluates shadows, contour curves, and border contrasts to detect protrusions against the curved intestinal wall.
-
High-performing AI models demonstrate sensitivity rates exceeding 95% for small bowel polyps and masses, serving as an indispensable safety net against human diagnostic oversight.
3. Clinical Efficiency: Shifting from 90 Minutes to 10 Minutes
The primary real-world benefit of AI-assisted capsule reading is the dramatic reduction in reading time without compromising clinical accuracy.
Plaintext
               WORKFLOW TIME COMPARISON: MANUAL VS. AI
+-------------------------------------------------------------------------+
| TRADITIONAL MANUAL REVIEW:                                              |
| [================================================= 60 - 90 Minutes ===] |
|                                                                         |
| AI-ASSISTED REVIEW:                                                     |
| [===== 10 - 15 Mins =====] (Up to 80% Time Saved!)                      |
+-------------------------------------------------------------------------+
The “Human-in-the-Loop” Paradigm
It is important to emphasize that AI in medical imaging is assistive, not autonomous. The software does not generate an unsupervised diagnosis and send the patient home. Instead, it operates on a “Human-in-the-Loop” model:
-
AI Pre-Processing: Once the patient’s data recorder is connected to the workstation, the AI processes the video in the background (typically taking 10 to 20 minutes to analyze the dataset).
-
Curated Thumbnail Presentation: When the doctor opens the case, they are not presented with a raw 10-hour video. Instead, they see an AI-curated summary showing the most significant anatomical landmarks and flagged abnormalities grouped by category (Bleeding, Ulcers, Polyps).
-
Rapid Physician Confirmation: The physician clicks through the flagged images. If an image shows a genuine lesion, the doctor saves it to the final diagnostic report with a single click.
-
Final Verification: The doctor scans through a high-speed, de-duplicated video stream to verify overall bowel cleanliness and transit times.
This streamlined workflow shortens the physician’s active reading time from 60–90 minutes down to just 10–15 minutes. For busy gastroenterology practices, this allows clinicians to read five to six capsule studies in the time it previously took to review just one, clearing hospital backlogs and expanding patient access.
4. Cloud Tele-Endoscopy: Breaking Down Geographic Barriers
Historically, capsule endoscopy workstations were isolated, standalone desktop computers physically located in major university teaching hospitals. A patient in a rural clinic had to travel to the city, or the rural clinic had to ship physical SD cards and USB drives through the mail to have a specialist review the data.
Cloud tele-endoscopy has decentralized this entire model.
Plaintext
                     CLOUD TELE-ENDOSCOPY NETWORK
+-------------------------------------------------------------------------+
| LOCAL RURAL CLINIC                  CENTRAL SPECIALIST HUB              |
| - Patient swallows capsule          - Expert Gastroenterologists        |
| - Recorder gathers data             - Reviews AI-flagged video on cloud |
| - Uploads to encrypted cloud --->   - Signs digital diagnostic report   |
|                                                                         |
|                [ Secure AES-256 Cloud PACS Gateway ]                    |
|             (Accessible via any authorized web browser)                 |
+-------------------------------------------------------------------------+
How Cloud-Based Reading Operates:
-
Local Acquisition: A community healthcare clinic or regional outpatient center administers the capsule exam and collects the data recorder from the patient.
-
Encrypted Cloud Upload: Instead of storing the gigabytes of video on a local PC, the software securely uploads the study to an enterprise cloud medical imaging server.
-
Remote Expert Analysis: An off-site gastroenterologist or reading specialist logs into the secure cloud portal using a tablet, laptop, or desktop. They review the AI-processed study and generate an electronic report from anywhere in the world.
-
Instant Diagnostic Turnaround: The rural clinic receives the finalized diagnostic report within hours, eliminating delays and enabling timely clinical intervention.
5. Hospital IT Integration: DICOM 3.0, PACS & EHR Connectivity
For modern hospital Chief Information Officers (CIOs) and healthcare IT administrators, new medical diagnostic equipment cannot exist in a digital silo. A capsule endoscopy system must integrate directly into the hospital’s enterprise software ecosystem.
Plaintext
                       ENTERPRISE IT INTEGRATION
+-------------------------------------------------------------------------+
| Hospital RIS / EHR  --> Queries Patient Worklist via DICOM MWL          |
| Capsule Workstation --> Captures Video & AI Diagnostic Bookmarks        |
| Enterprise PACS     --> Archives Still Images & Video Clips (DICOM Store)|
| Electronic Record   --> Attaches Final PDF Report to Patient Chart       |
+-------------------------------------------------------------------------+
-
DICOM Modality Worklist (MWL): Eliminates manual data entry. The capsule workstation queries the hospital’s Radiology Information System (RIS) or Electronic Health Record (EHR), automatically populating patient demographics, accession numbers, and clinical indications with zero typing errors.
-
DICOM Storage & Structured Reporting (SR): When the doctor completes the review, the selected diagnostic images, short video loops of identified lesions, and the clinical findings report are transmitted directly to the hospital’s central PACS (Picture Archiving and Communication System).
-
Cybersecurity & Compliance: Leading cloud tele-endoscopy platforms employ AES-256 bit encryption for data storage and TLS 1.3 encryption for network transmission, maintaining strict compliance with international patient privacy frameworks, including HIPAA (Health Insurance Portability and Accountability Act) and GDPR (General Data Protection Regulation).
6. Comparison: Traditional Video Players vs. AI-Powered Cloud Workstations
When evaluating software capabilities during equipment procurement, hospital committees should reference this side-by-side comparison:
| Operational Feature | Traditional Legacy Workstation | Next-Gen AI Cloud Workstation |
| Video Review Method | Continuous, unassisted video playback | AI-assisted redundant frame filtering & lesion sorting |
| Average Reading Time | 60 to 90 minutes per patient | 10 to 15 minutes per patient |
| Active Bleeding Detection | Basic color detection (Frequent false alarms) | Deep learning vascular & bleeding pattern recognition |
| Polyp & Ulcer Detection | Dependent 100% on human eye vigilance | Automated bounding boxes highlighting suspect lesions |
| Data Storage Location | Local internal hard drive only | Secure cloud PACS with automatic off-site archiving |
| Remote Tele-Reading | Not supported (Must be on physical PC) | Fully supported via secure web portals & remote access |
| EHR / PACS Connectivity | Often requires proprietary third-party bridges | Native DICOM 3.0 store, worklist, and report export |
| Software Updates | Manual technician visits / USB patches | Seamless over-the-air (OTA) cloud software upgrades |
7. Open Software Architecture: A Smart Procurement Principle
When purchasing capsule endoscopy systems, hospital procurement teams should prioritize open, interoperable software architectures.
Some medical device manufacturers deliberately lock their capsule reading software behind closed, proprietary ecosystems. In these models, exporting images requires expensive software licenses, connecting to the hospital PACS requires costly custom IT integration, and upgrading the software incurs recurring annual fees.
The Value of Open, Subscription-Free Engineering
Forward-thinking manufacturers, such as UMY Medical Equipment Co Ltd, advocate for open, clinically accessible diagnostic software. By ensuring that capsule reading workstations feature native DICOM 3.0 export compliance and direct compatibility with standard hospital IT networks, healthcare facilities protect their technology investments.
Furthermore, partnering with manufacturers that bundle intuitive software with regular algorithm improvements—rather than imposing forced monthly subscriptions—ensures that clinics can expand their screening services while keeping operating costs strictly predictable.
Frequently Asked Questions (FAQ)
Q1: Can AI software miss a tumor or bleeding ulcer in capsule endoscopy?
While modern AI algorithms achieve sensitivity rates between 95% and 99% in clinical trials, no software is infallible. Poor bowel preparation (stool debris, dark bile, or air bubbles) can obscure lesions from both the camera and the AI. This is why the final interpretation always rests with a qualified gastroenterologist who reviews the entire study alongside the AI’s suggestions.
Q2: Does AI software increase the rate of “false alarms” (false positives)?
Early generations of red-detection software flagged hundreds of harmless food particles and normal mucosal folds. However, modern convolutional neural networks analyze contextual shapes, tissue edges, and vascular architecture, drastically reducing false positives and presenting doctors with highly relevant clinical targets.
Q3: What computer hardware is required to run AI capsule reading software?
Because deep learning models require substantial processing power to analyze 60,000 images, modern workstations typically utilize high-performance multi-core processors paired with dedicated medical-grade Graphic Processing Units (GPUs). Alternatively, cloud-based tele-endoscopy platforms handle the processing on remote servers, allowing doctors to review cases on standard laptops or tablets.
Q4: Is tele-endoscopy safe from cybersecurity breaches?
Yes, provided the software adheres to modern healthcare data standards. Data streams must use end-to-end encryption (such as AES-256), multi-factor authentication (MFA) for clinician logins, and automatic session logouts to protect sensitive Patient Health Information (PHI).
Q5: How does AI handle transit landmarks like the stomach and cecum?
Advanced AI software automatically recognizes anatomical transitions. It identifies the first frame where the capsule passes through the pyloric sphincter into the duodenum, and the exact frame where it crosses the ileocecal valve into the cecum. The software automatically calculates gastric transit time and small bowel transit time, saving the doctor from manually scrubbing through the video to find these landmarks.
Summary
The marriage of Artificial Intelligence and Wireless Capsule Endoscopy has resolved the single greatest drawback of non-invasive GI imaging: the exhausting, time-consuming manual review process.
By filtering out tens of thousands of redundant frames, highlighting critical pathologies, and connecting seamlessly to hospital PACS and cloud tele-medicine networks, smart software turns capsule endoscopy into a rapid, scalable, and highly accurate diagnostic solution for healthcare systems worldwide.